

Area-Specific Revision Design
Revision must be redesigned area by area
Abdomen, arm, thigh and hip break down in different ways. Even when it looks like the same dent or adhesion, the pulling direction, fat-layer thickness, skin slack and contour connection differ by area — so the design criteria must differ too.
Is This You?
Which area bothers you most?
- Abdominal folding and height differences
- Arm scar-adjacent pulling and rippling
- Thigh vertical grooves and inner pulling
- Hip / under-buttock line breaks and dimples
- A different deformation pattern in each area
- Not knowing where to start

Direct Answer
What is region-specific revision design?
It means not treating the irregularity, depression, asymmetry or broken contour left after liposuction as one single problem. The abdomen, arm, thigh and hip are each assessed on their own tissue condition, and the method and the order of correction follow from that assessment.
Two areas can look alike and still need different treatment. Fat that was left behind, tissue that was taken too superficially or too aggressively, scarring and fibrosis that pull on the surface, and skin that has not retracted are not always easy to tell apart from the outside.
- Irregular contours and asymmetry are among the known possible outcomes after liposuction, and the possibility of revision surgery is listed alongside them.
- The cause is rarely single. The amount and depth of tissue removed, scarring and fibrosis, how far the skin retracts, fat deficiency and the healing process can all play a part.
- So a revision plan does not start by choosing a technique. It starts by separating the causes of what is left.
- Contour cannot be judged reliably while swelling remains. It matters to wait until swelling has settled enough for the contour to be assessed, and some literature recommends allowing at least around six months before a contour-correction revision is planned.
- Skin thickness, fat-layer depth, movement and scar position differ by area, so a method used in one region cannot simply be transferred to another.
- Revision can be expected to improve the contour, but a perfectly matched left and right side, or a result with no trace of the previous surgery, cannot be promised.
Why It's Different
Different areas mean a different correction order
Revision is not applying one method to every area. Abdomen, arm, thigh and hip differ in skin thickness and movement, fat-layer depth, scar location and contour connection. NB first identifies which problem comes first in which area, then designs the correction order.
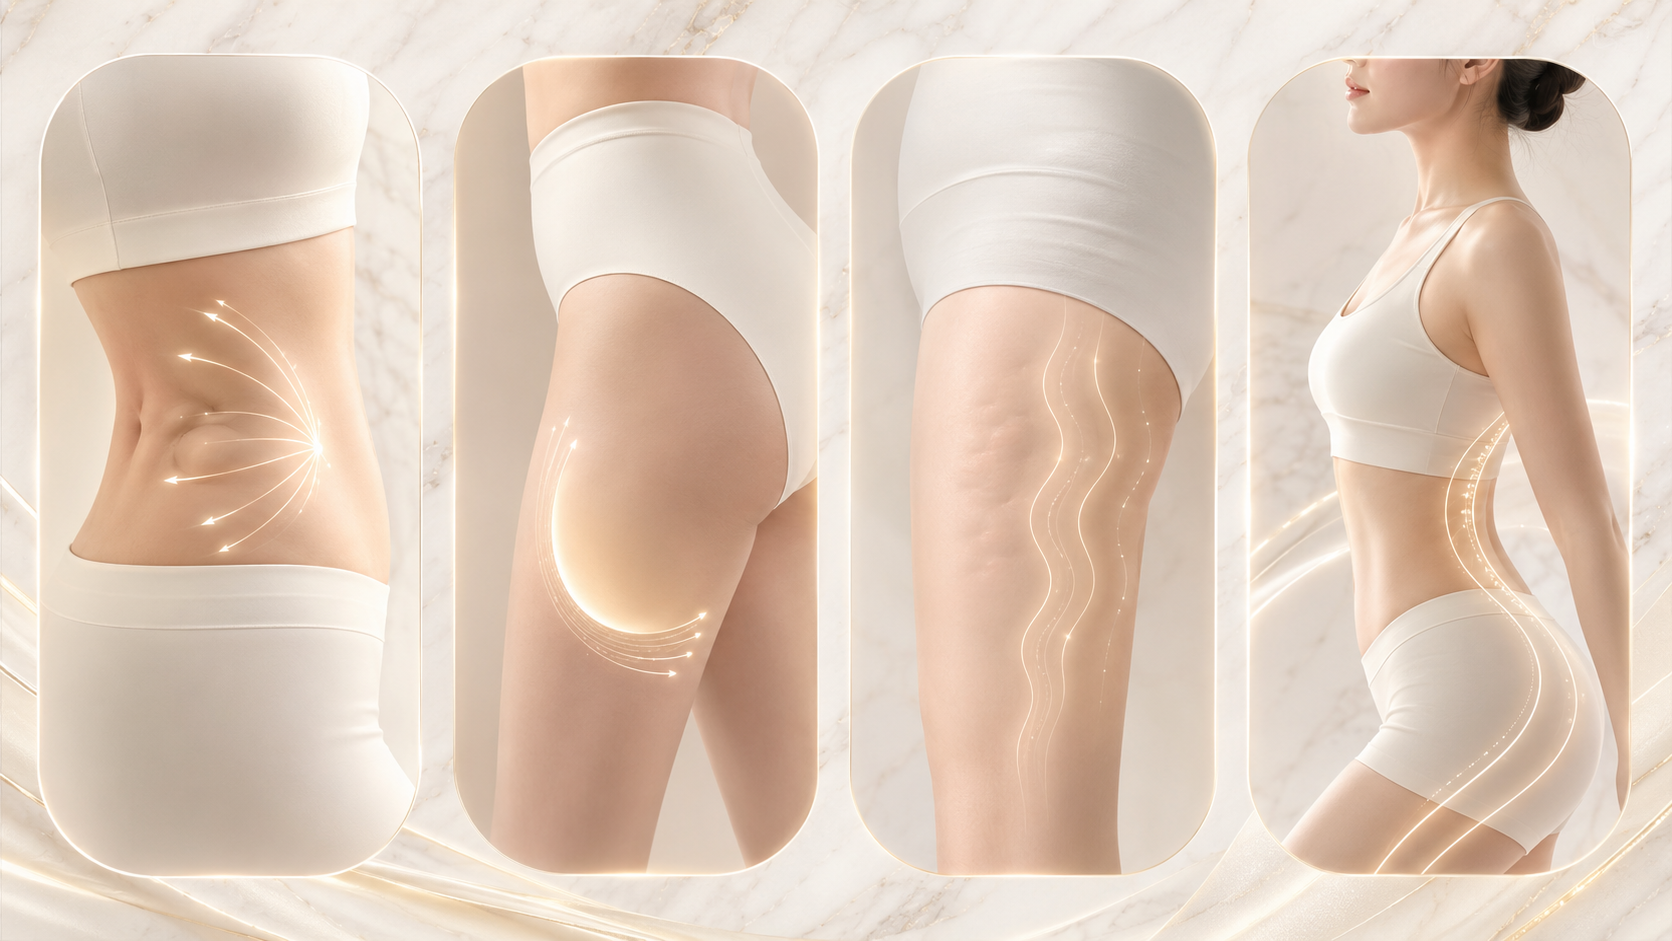


Area Patterns
Which area needs redesign?
Abdomen, arm, thigh and hip break down in different ways.
Assessment
What does a revision assessment look at?
A revision plan is not decided from a photograph. We look at how the contour changes with posture, which direction the tissue pulls on movement, and how firmness and thickness differ on palpation.
- Visible contour — how the line changes standing, sitting and in movement.
- Palpation — firmness, mobility, overall difference in thickness, and how the tissue responds to pressure.
- Scar and pulling findings — whether a previous surgical site feels firm, and whether the surface is drawn in with it.
- Fat-layer thickness and deficiency — separating what was left behind from what was over-resected.
- Skin condition — thickness, elasticity and retraction, and whether adjusting fat alone can address it.
- Connection to neighbouring contours — the flank, the axilla, and the hip-to-thigh transition are reviewed together.
When needed, ultrasound helps check skin and subcutaneous fat thickness, the boundary between layers, and fat distribution. It is not a device that definitively diagnoses every adhesion or predicts the result in advance. Measurements can vary with examination conditions, so they are read together with the clinical examination.
NB Approach
The order we redesign area by area
- 1. Release — first check whether the pulling layer must be released.
- 2. Smooth — see whether surface texture and contour bends need refining.
- 3. Support — assess whether missing volume or sunken areas need support.
- 4. Reconnect — reconnect broken surrounding lines for a natural flow.
- 5. Recovery Planning — plan management considering each area’s recovery load and re-adhesion possibility.

By Region
Abdomen, arms, thighs, hips — each distorts in its own way.
Even when it looks like the same adhesion or dent, the abdomen, arms, thighs, and hips differ in skin thickness, fat-layer depth, movement, scar location, and how they connect to the surrounding lines. Mapping each region's distortion pattern first is what reveals the revision direction.
Skin thickness, movement, scar position and the connection to neighbouring contours genuinely differ by area and are checked in consultation. There is, however, little research directly comparing which method works better in which region. What follows describes what is reviewed together in each area; it does not mean a separate technique exists for each one.


Arm Revision Design
- Inner-arm surface irregularity
- Tightness around scars
- Uneven arm-to-armpit transition
- Wavy-looking arm line
The arm has thin skin and moves a lot, so even small scar-area tightness or surface irregularity can make the line look noticeably off. Arm revision looks not only at the inner arm but also at how it connects to the armpit, bra line, and the side of the upper body.


Abdomen Revision Design
- Upper/lower abdomen height difference
- Folding
- Firm adhesion
- Surface unevenness
- Dents around scars
The abdomen looks different standing versus sitting. Folding, firmness, the height difference between the upper and lower abdomen, and dents around scars all have to be read together to judge whether to remove more, release adhesions, or rebalance the surrounding lines.


Thigh Revision Design
- Vertical dents
- Inner-thigh tightness
- Uneven outer line
- Irregularity confused with cellulite
- Hip-to-thigh connection
The thigh requires distinguishing the difference in fat layers between the inner and outer side, vertical-looking dents, and surface irregularity that can be confused with cellulite. Thigh revision considers not just the dented area but the whole lower-body line continuing toward the hip and knee.


Hip & Buttock Revision Design
- Dimples
- Dimple-type dents
- Broken under-buttock line
- Hip-to-thigh imbalance
- Mixed fat loss and adhesion
On the hip and under-buttock line, even a small dimple or dimple-type dent can make the whole lower-body proportion look broken. Buttock revision designs not just a single dented point but the connection across hip volume, the under-buttock line, and the thighs.

Limitations
What revision can and cannot do
Revision reduces what is left. It does not return the body to its state before the first operation, and it does not make the two sides identical. The realistic range is discussed before anything is planned.
- Revision also involves a recovery process with swelling, bruising, pain, altered sensation and scarring.
- Because it starts in tissue that already carries scarring and fibrosis, the degree of improvement can be more limited than in a first operation.
- Part of any grafted fat is resorbed, and the amount cannot be known in advance. A further procedure is sometimes needed.
- Where the deformity is severe or tissue change is extensive, a single correction may not be enough and further correction may be needed.
- Where skin elasticity is substantially reduced, adjusting fat alone may not make the surface smooth.
- Bodies are not symmetrical to begin with. A difference between the two sides can remain after revision.
- Revision is not always necessary. Some changes improve with time, and there are cases where waiting is the better course.
This page provides general medical information. It is not an individual diagnosis or a recommendation of treatment. Whether and how any method applies is decided after your current condition is examined in consultation.
Before & After
Area-specific revision cases
Deformation type
Area

Lifestyle
“Daily life where you no longer feel the need to hide your body line”

Where To Go Next
Toward what's closer to your concern
If pulling or firmness stands out
If an adhered, pulling feeling is central, an adhesion / fibrosis assessment may be needed first.
If dents, grooves or dimples concern you more
If sunkenness, dimple-like dents or unevenness are central, dent / irregularity type classification is needed.
If above-knee wrinkles or laxity concern you
Above-knee wrinkles and laxity are better viewed separately through age-related skin laxity and BodyTite tightening.
FAQ
Frequently Asked Questions
Q. Is revision more difficult than the first surgery?
Revision works on tissue that already carries scarring and fibrosis, so understanding the current state accurately matters more than it does in a first operation. The cause of what remains is also rarely single: fat left behind, areas over-resected, a pulling scar and insufficient skin retraction have to be separated first, because there are cases that removing more fat will not solve.
Q. When is the right time for revision?
Contour cannot be judged while swelling remains. It matters to wait until swelling has settled enough for the contour to be assessed, and some literature recommends allowing at least around six months before a contour-correction revision is planned. Healing speed and tissue condition vary between people, so NB reviews your current state first and discusses timing with you.
Q. Can I have revision if my first surgery was done elsewhere?
The current tissue condition matters more than where the previous surgery was done. NB evaluates the cause of the current contour issue and plans a correction direction based on recovery potential.
Q. How far can revision results be predicted?
The degree of change can vary with tissue condition and the healing process. Rather than promising a result, NB assesses the current state as accurately as possible before surgery and explains the range that can reasonably be expected. We do not promise identical left and right sides, or a result that leaves no trace.
Q. Can several areas be revised at the same time?
This depends on tissue condition and recovery burden. Multiple areas may be considered in some cases, but NB prioritizes stable contour recovery over an excessive treatment range.
Q. Are there possible side effects after revision?
Revision also involves a recovery process that can include swelling, bruising, pain, altered sensation, inflammation and scarring. Contour that remains uneven, a difference between the two sides, and uneven resorption in a grafted area are all recognised possibilities. Where tissue damage was already present, managing recovery matters especially, so NB follows the area until the contour settles.
Q. How is revision cost determined?
Revision cost depends on the current tissue condition and correction range rather than the area name alone. Adhesion severity, volume deficiency, and the needed correction method are reviewed during consultation.
Q. Are above-knee wrinkles handled on this page?
Wrinkling and laxity above the knee are usually driven by age-related skin laxity rather than by adhesion or a fat problem, so the approach differs. This page covers revision design for the abdomen, arm, thigh and hip; knee-line tightening is covered on a separate page.
Q. Why look at the flanks during an abdominal revision?
The abdomen and flanks form one continuous curve. Reworking only the front can leave a step in thickness where the two meet, so the line may read better from the front yet still break in profile. NB reviews the abdomen, flanks and waist together during revision planning before deciding where and how much to remove.
MEDICAL REVIEW
Medically reviewed by
CHO HONG KYU, Chief Director
Plastic Surgeon
Last reviewed ·
REFERENCES
References
- American Society of Plastic Surgeons - Liposuction Risks and Safety
- Dixit VV, Wagh MS. Unfavourable outcomes of liposuction and their management. Indian Journal of Plastic Surgery, 2013
- Ferry AM et al. Avoidance and Correction of Deformities in Body Contouring. Seminars in Plastic Surgery, 2021
- Aljerian A et al. Complications of Aesthetic Liposuction Performed in Isolation: A Systematic Literature Review and Meta-Analysis. Plastic Surgery (Oakville), 2024
- Neagu M, Neagu A. A Decade of Progress in Ultrasound Assessments of Subcutaneous and Total Body Fat: A Scoping Review. Life (Basel), 2025
- Yang M et al. Difficulty of Severe Post-liposuction Infragluteal Deformity Correction With Autologous Fat Transplantation: A Case Report. Frontiers in Surgery, 2022

After surgery, with you through recovery
- 01VersaClear light therapy2 sessions
- 02Ucell standing-wave therapy2 sessions
- 03Radiofrequency care4 sessions
- 04
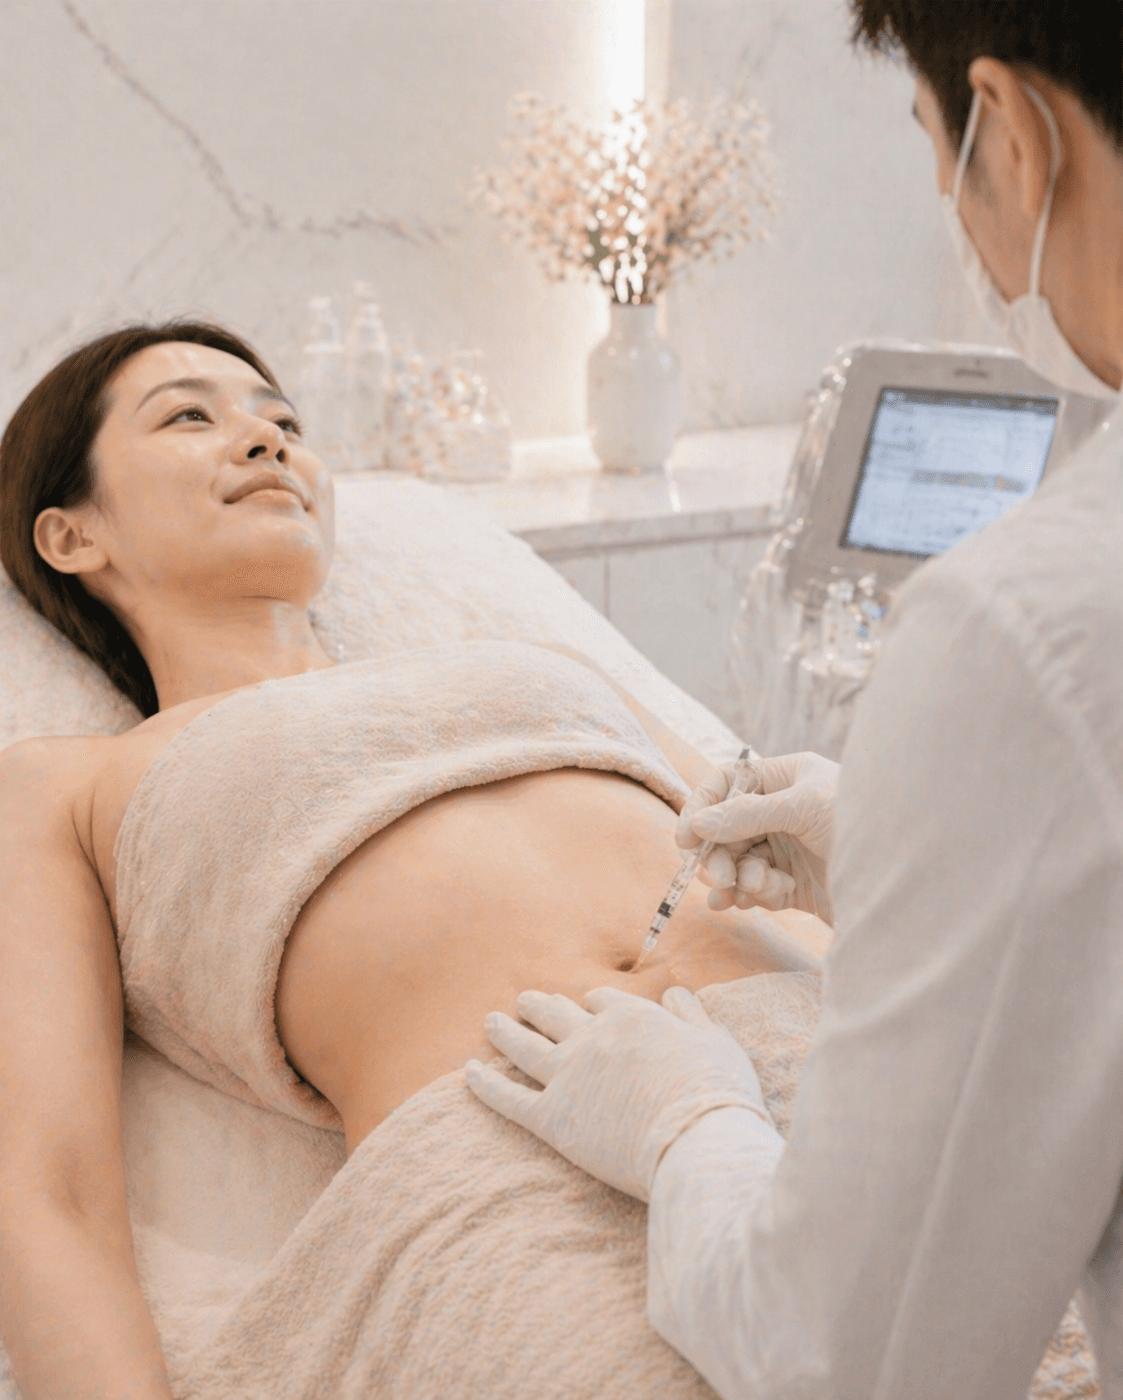 Soft-meso injection· Performed by the doctor2 sessions
- 05
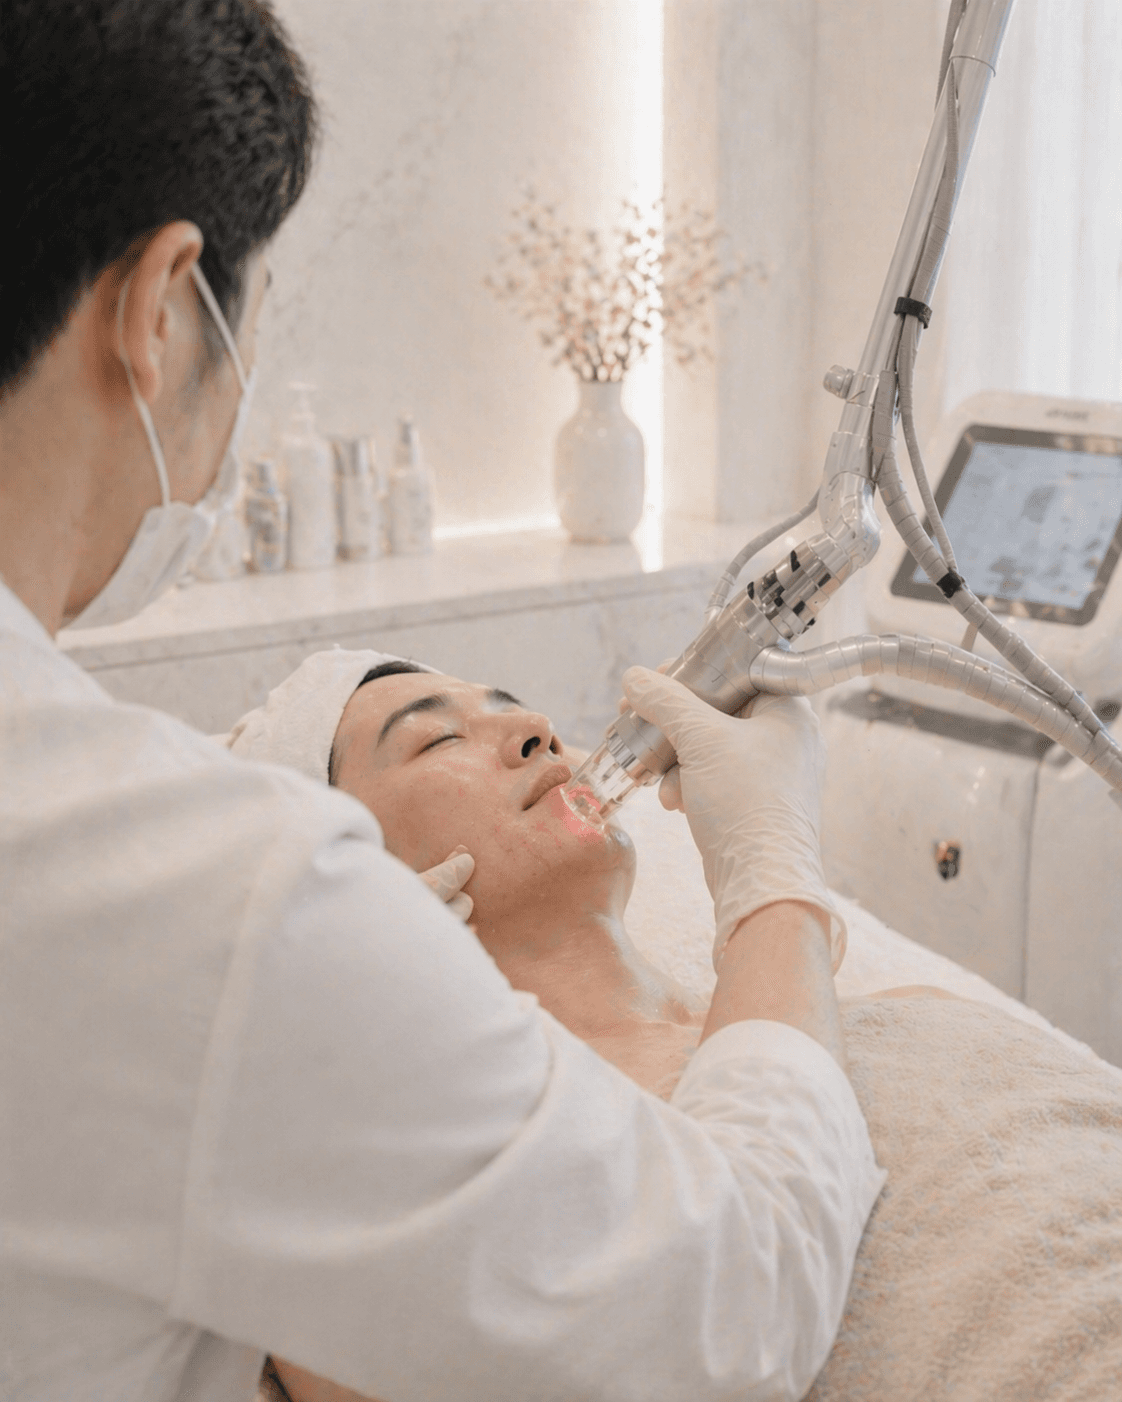 Fraxel scar laser· Performed by the doctor2 sessions
Basic aftercare is provided as a standard programme of 12 sessions in total — 4 swelling-care, 4 radiofrequency, 2 scar-laser and 2 meso-injection sessions. Actual scheduling and completion may vary depending on your ability to attend.
If care is needed beyond the basic aftercare, NB surgery patients receive a 50% discount on the standard price.
Legal Notice
※ If care cannot be provided due to reasons such as equipment malfunction, the affected care item may not be offered; as a service item, it is non-refundable.
※ Depending on your constitution and healing process, side effects such as swelling, bruising, inflammation, and scarring may occur after surgery.

NB Revision Design